How many men had mood changes?
A randomized, blinded study enrolled 56 healthy men aged 20–50. They received testosterone and placebo in separate six-week periods. Researchers measured manic symptoms with the Young Mania Rating Scale, which assesses features such as elevated mood, irritability and increased activity.
| Mood response | Testosterone50 periods | Placebo50 periods |
|---|---|---|
| Moderate or marked response | 16%8 of 50 | 2%1 of 50 |
| Minimal response | 84%42 of 50 | 98%49 of 50 |
Pope, Kouri and Hudson (2000), Results. The authors classified responses after collecting the data: minimal scores below 10, moderate 10–19, marked 20 or higher.
The eight testosterone responses included six moderate and two marked responses. Placebo produced one moderate response and none marked. Most responses were minimal. These were short-term symptom ratings, not eight new bipolar diagnoses or a lifetime risk estimate. The trial supports a drug effect on mood; it does not measure a teenager’s brain development.
The scope here is high-dose anabolic-androgenic steroid use for physique or performance. These findings do not supply a risk estimate for medically supervised testosterone replacement or for anti-inflammatory corticosteroids.
For someone starting at 19, the unanswered question is lasting change. Human studies report associations with brain structure, impulsivity, anxiety and narcissistic traits. They do not establish that starting at that age stops brain growth, causes narcissistic personality disorder or produces permanent bipolar disorder.
Trenbolone is one part of this broader question. Our trenbolone and mental-health article examines its specific survey evidence separately.
What brain scans actually show
A 2017 MRI study compared 82 men with at least a year of cumulative anabolic-steroid use with 68 weightlifters who had not used them. Users had smaller average cortical and gray-matter volumes. The comparison below shows the percentage differences, with the exact measurements underneath:
| Brain region | Average in users |
|---|---|
| Cerebral cortex | 4.4% lowerUsers: 506,914 mm³ Nonusers: 530,158 mm³ |
| Total gray matter | 3.8% lowerUsers: 678,682 mm³ Nonusers: 705,416 mm³ |
These are differences between group averages, not percentages of brain tissue lost by individual men. TitrateLab calculated them from the published raw means. The paper’s statistical analyses accounted for age and head size. Bjørnebekk et al. (2017), Table 3

There were no pre-use scans establishing each man’s starting point. Smaller average volume does not by itself identify the cause, measure everyday impairment or show arrested development at 19. It is a concerning association that needs follow-up, not a diagnosis from a brain scan.
A later study compared 130 users with 99 nonusers using an MRI-based estimate of brain age. Users had higher predicted brain-age gaps. Among 76 men with repeated scans about 3.5 years apart, the overall user group did not show faster brain aging; longer exposure was associated with acceleration. A model’s “brain age” is not a diagnosis of dementia or a count of years someone has lost. Bjørnebekk et al. (2021)
What is known about starting young?
The most directly relevant human study was small. Seventy-one adult male steroid users completed questionnaires; 22 underwent cognitive testing. Earlier initiation was associated with greater impulsivity and more sensitivity to some on-cycle attention effects. This was a comparison of existing users, without measurements before their first exposure. Hildebrandt et al. (2014)
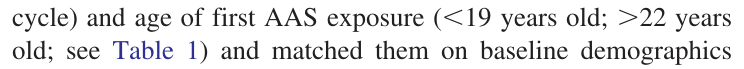
That age split matters: the cognitive comparison did not test starting specifically at 19. Nor can it show that steroid exposure created every difference between the groups. The men could differ in traits or circumstances that preceded their use.
Normal developmental research shows that brain structure continues changing across adolescence and early adulthood. In four longitudinal samples, 391 participants contributed 852 scans across ages 8–30. That supports taking development seriously; it does not establish a birthday at which high-dose steroid use becomes neurologically safe. Mills et al. (2016)
Experiments can investigate mechanisms more directly, but their subjects matter. In developing rat cortical cells, testosterone, nandrolone and trenbolone reduced the growth of neuronal extensions under the tested conditions. Trenbolone also reduced cell viability. A dish of rat cells cannot supply a percentage risk of permanent brain damage in a 19-year-old person. Zelleroth et al. (2021)
Anxiety and depression: symptoms vary
In a 2024 comparison of 25 steroid-using male bodybuilders with 25 nonusing bodybuilders, seven users screened in the mild-anxiety range. Seven screened in the mild or moderate depression ranges. Neither outcome was recorded in the comparison group. These are two symptom measures; the counts must not be added to claim 14 different men were affected. Karagun and Altug (2024)
| Screening result | Steroid users25 men | Nonusers25 men |
|---|---|---|
| Mild anxiety symptoms | 28%7 of 25 | 0%0 of 25 |
| Mild/moderate depression symptoms | 28%7 of 25 | 0%0 of 25 |
The study used the Beck Anxiety and Depression Inventories. Seven of 25 is 28%, but that figure describes this small sample. It is not the probability that steroids will cause an anxiety disorder or depression in any user. Participants used different compounds, and researchers did not establish their pre-use symptom levels.
The prospective HAARLEM study provides useful counterevidence. It followed 100 men before, during and after steroid cycles. Agitation was reported during use, yet overall questionnaire scores for depression, wellbeing and quality of life did not change significantly. Smit et al. (2021)
A group average can remain stable while some people have difficult reactions. Equally, a higher symptom score in one survey does not establish that every user deteriorates. Study design, timing and the outcome being measured all affect the answer.
Can steroids cause bipolar disorder or narcissism?
The evidence supports distinctions that headline labels often blur. Elevated-mood symptoms during drug exposure are not enough to diagnose an independent, enduring bipolar disorder. Establishing that diagnosis requires a clinical history, including episodes outside substance exposure. The testosterone trial measured a drug response, not lifetime psychiatric outcomes.
A 2025 questionnaire study recruited 319 male bodybuilders and linked current anabolic-steroid use with higher narcissism and aggression scores. The authors explicitly left the direction of cause unresolved: traits could precede use, follow it, or share other explanations. A narcissism score is not a diagnosis of narcissistic personality disorder. Ceto et al. (2025)

The same caution applies to an individual story. Aggression, grandiosity, anxiety or relationship problems may deserve assessment, but they cannot tell us retrospectively which compound caused them or whether the change will last. Research about group averages cannot diagnose a particular person.
Where trenbolone fits
The clearest trenbolone comparison we reviewed involved 237 men who reported past-year injectable trenbolone use and 909 other steroid users. Loss of interest was reported by 55 of 237 versus 73 of 909; rapid mood changes by 56 versus 86. These were self-reported concerns, with no adjustment for dose, cycle length or combinations of steroids. Bonenti et al. (2026)
Those figures cannot be applied to every anabolic steroid, and the testosterone trial cannot establish trenbolone’s effects. See the full trenbolone comparison, original study excerpts and downloadable data for that evidence on its own terms.
Sources and methods
TitrateLab reviewed primary papers and indexed primary-source records on September 29, 2026. Searches addressed anabolic steroids, adolescent initiation, mood, anxiety, narcissism, brain structure and trenbolone. This is a targeted narrative review, not a systematic review or pooled estimate. Most participants were adult men; the results are not universal estimates for women, teenagers or medical hormone treatment.
We checked the testosterone response counts against the publisher’s Results section; the MRI means, age-selection criteria, anxiety/depression results and personality-study limitations against original papers. The brain-age, HAARLEM, developmental and cell-study summaries also use indexed primary records. These sources differ in design and may include overlapping research cohorts; we have not added their participants together or treated them as independent replications of one result.
Percentages divide the reported count by that study’s denominator. MRI differences use (comparison mean − user mean) ÷ comparison mean × 100, rounded to one decimal place. They describe group averages, not changes within people. Download the extracted measurements and calculation notes.
The study images are genuine, unaltered rectangular excerpts. Short quotations from the MRI and age-initiation papers are attributed beside each image; the Ceto excerpt is reproduced under CC BY 4.0. Full papers are linked at their sources.
Prepared with AI assistance for the TitrateLab Research Desk; no clinical review is claimed. See our evidence methodology, research library and corrections/contact page.